

 English

Pituitary pars intermedia dysfunction (PPID), previously called equine Cushing’s disease, is a common hormonal disorder in older horses. It affects the pituitary gland and can cause changes throughout the body, including delayed or abnormal coat shedding, increased thirst and urination, muscle loss, and a greater risk of laminitis.
PPID is progressive, but early recognition and appropriate management can help maintain a horse’s quality of life. Diagnosis typically involves blood testing for adrenocorticotropic hormone (ACTH), and the primary medical treatment is a medication called pergolide. Some veterinarians may prescribe cabergoline based on the individual horse’s needs.
Nutrition and routine preventive care are also important for managing horses with PPID, particularly for those with concurrent insulin dysregulation or a history of laminitis.
Read on to learn about the causes, signs, diagnosis, treatment, and long-term management of PPID in horses.
What Is Equine Cushing’s Disease?
Equine Cushing’s disease is the historical name for pituitary pars intermedia dysfunction, a condition involving the pituitary gland at the base of the horse’s brain. The pars intermedia is one region of this gland and produces hormones that influence several body functions.
In a healthy horse, dopamine-producing neurons (nerve cells) in the hypothalamus inhibit activity in the pars intermedia. In cases of PPID, these neurons progressively degenerate, reducing dopaminergic control of the gland. Oxidative damage is associated with this age-related neurodegeneration, although its root cause is not fully understood. [1]
Loss of this inhibition causes enlargement of the pars intermedia, which subsequently overproduces hormones derived from the precursor protein pro-opiomelanocortin (POMC). These hormones include: [1]
- Adrenocorticotropic hormone (ACTH)
- Alpha-melanocyte-stimulating hormone (a-MSH)
- Beta-endorphin
- Corticotrophin-like intermediate peptide (CLIP)
Altered production of these hormones contributes to the clinical signs of PPID in affected horses. [1]
Table 1. Pituitary pars intermedia dysfunction (PPID) at-a-glance
| Category | Key Information |
|---|---|
| Definition |
|
| Primary Cause |
|
| Risk Factors |
|
| Onset |
|
| Signs |
|
| Severity |
|
| Diagnosis |
|
| Treatment |
|
| Recovery Time |
|
| Prognosis |
|
| Prevention |
|
Clinical Signs
The most characteristic sign of PPID is an abnormal hair coat. Affected horses may grow a long or shaggy coat and shed late or incompletely when transitioning from winter to summer. This condition is called hypertrichosis, although it is not present in every horse with PPID. [1]
Other signs associated with PPID include: [1]
- Excessive sweating
- Abnormal fat distribution
- Loss of topline musculature
- Laminitis
- Weight loss
- Recurrent infections
- Behavioral changes, particularly lethargy
- Poor wound healing
- Increased urination and thirst
- A pot-bellied appearance associated with muscle loss
- Bulging fat pads above the eyes
- Lordosis, or a swaybacked posture
- Infertility
Many of these signs can occur with other conditions. Clinical signs alone cannot confirm PPID, therefore veterinary assessment and diagnostic testing are important before treatment begins. [1]
What's your top priority with your horse's health?

What's your top priority with your horse's health?
Risk Factors
PPID is the most common endocrine disorder in older horses and ponies, and age is its primary risk factor. Around 20% of horses and ponies older than 15 years have PPID, with prevalence rising to approximately 30% by 30 years of age. [2]
Research has not established a consistent difference in risk between males and females. Evidence is also mixed on whether ponies, donkeys, or mules have a higher or lower risk than horses. Age remains the clearest predictor of PPID. [1]
Laminitis & PPID
Some horses with PPID also have insulin dysregulation, which may include insulin resistance, excessive insulin release after consuming sugar or starch, or high pre-meal insulin.
The relationship between PPID and insulin dysregulation is not fully understood, but laminitis risk is higher in horses with both conditions. [1] Estimates suggest that 25% to 50% of horses with PPID develop laminitis during their lifetime. [1]
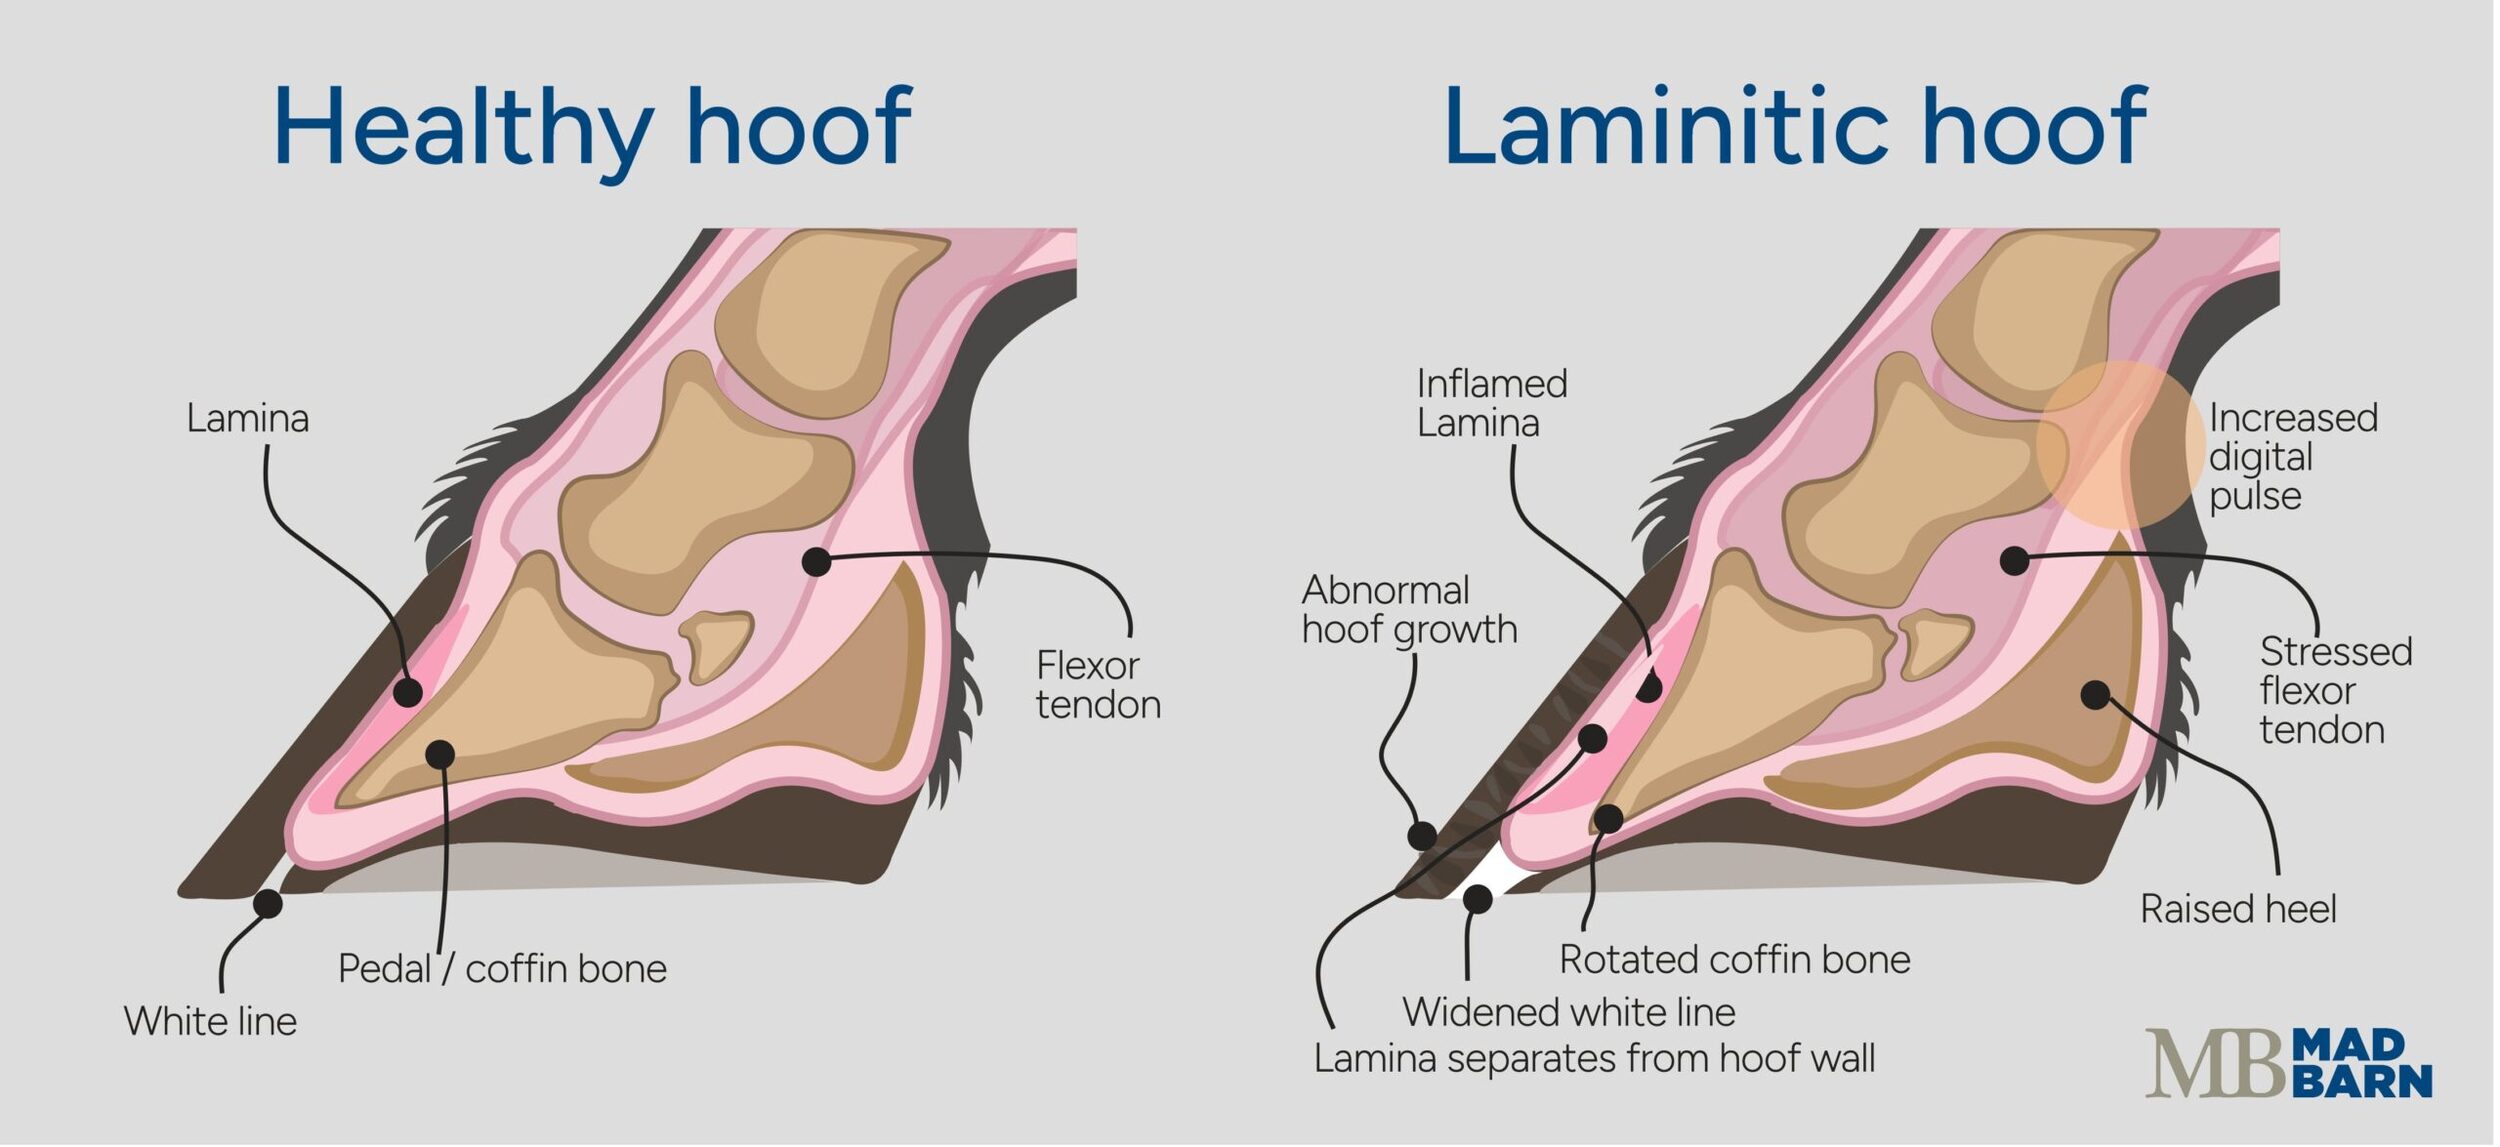 Illustration: Dr. Ana Mesa, PhD
Insulin helps cells take up glucose from the bloodstream to use as energy. When tissues respond poorly to insulin, the pancreas may release more to maintain appropriate glucose use. As a result, a horse can have high insulin concentrations even when blood glucose remains within normal range.
Laminitis occurs when the lamellae that suspend the coffin bone within the hoof become damaged and begin to fail. Severe laminar failure can allow the coffin bone to rotate or sink within the hoof capsule, causing intense pain.
An affected horse may shift weight away from the front feet, stand with the forelimbs stretched forward (“sawhorse stance”), or be reluctant to move.
 Sawhorse Stance Illustration: Dr. Ana Mesa, PhD
Sustained high insulin concentrations can induce laminitis, although the exact mechanism is still being investigated. [4] The relationship between insulin dysregulation and laminitis has been more extensively studied in horses with equine metabolic syndrome (EMS) than in horses with PPID. In EMS horses, elevated insulin or insulin resistance may influence glucose availability to laminae, blood flow to the hooves, and oxidative stress. [5]
When to Call the Veterinarian
Contact your veterinarian if an older horse develops delayed shedding, unexplained muscle loss, increased drinking or urination, recurrent infections, or other signs consistent with PPID. These changes are not specific to the condition, and a veterinary examination helps determine which tests are appropriate.
Suspected laminitis requires prompt veterinary attention. Call your veterinarian immediately if your horse shows any of the following signs:
- Sudden or severe lameness
- Reluctance to walk, turn, or lift a foot
- A rocked-back stance or repeated weight shifting
- Unusual heat in the hooves or strong digital pulses
Early assessment can limit further hoof damage and guide pain control, hoof support, diagnostic testing, and dietary management. Horses with PPID should also be evaluated for insulin dysregulation because concurrent hyperinsulinemia affects laminitis risk and management. [1][4]
Diagnosis
Veterinarians diagnose PPID in horses by considering the horse’s age, medical history, and clinical signs alongside blood tests that measure hormone levels.
The two main diagnostic tests are a baseline ACTH test and a thyrotropin-releasing hormone (TRH) stimulation test. Blood test results should not be interpreted in isolation.
ACTH levels naturally vary with the seasons and can also be affected by breed, illness, stress, pain, sample handling, and the laboratory testing method. For this reason, veterinarians interpret test results using seasonally adjusted reference ranges and consider the horse’s clinical signs when determining whether PPID is present. [6]
Baseline ACTH Test
The baseline ACTH test measures the horse’s circulating ACTH under normal circumstances without administering a stimulating agent.
A veterinarian collects a blood sample, which is handled under controlled conditions and submitted to a diagnostic laboratory. The result is compared with season- and assay-specific reference intervals to assess whether PPID is unlikely, possible, or likely. [6]
Results within the interpretive zone do not confirm or exclude PPID. The veterinarian considers the horse’s age, clinical signs, and other relevant factors when deciding whether to perform additional testing, begin treatment, or retest later.
Healthy Arabians and donkeys may have higher ACTH concentrations throughout the year, while Welsh and Shetland ponies may have higher concentrations during autumn. These breed-related differences can complicate interpretation, reinforcing the need to consider the whole clinical picture. [6]
Table 2. Example seasonal reference ranges for baseline ACTH. [6]
The following values are the 2023 Equine Endocrinology Group interpretive thresholds for the Immulite 2000xpi analyzer in the Northern Hemisphere. Laboratories may use different assays and reference intervals.
| Time of year | PPID unlikely | Interpretive zone | PPID likely |
|---|---|---|---|
| January to June | < 15 pg/mL | 15 to 40 pg/mL | > 40 pg/mL |
| July | < 15 pg/mL | 15 to 50 pg/mL | > 50 pg/mL |
| August | < 20 pg/mL | 20 to 75 pg/mL | > 75 pg/mL |
| September to October | < 30 pg/mL | 30 to 90 pg/mL | > 90 pg/mL |
| November | < 15 pg/mL | 15 to 50 pg/mL | > 50 pg/mL |
| December | < 15 pg/mL | 15 to 40 pg/mL | > 40 pg/mL |
TRH Stimulation Test
During a TRH stimulation test, horses suspected of having PPID are given thyrotropin-releasing hormone (TRH), which stimulates the pituitary gland to release ACTH.
Horses with PPID generally have an exaggerated ACTH response because the abnormal pars intermedia releases more ACTH after stimulation than a healthy gland.
Veterinarians may use the TRH stimulation test for: [6]
- Horses with few, mild, or early clinical signs
- Horses younger than a typical PPID patient
- Horses with baseline ACTH results in the PPID-unlikely or interpretive range despite suggestive signs
To perform the test, the veterinarian collects a baseline blood sample, administers TRH intravenously, and collects another sample exactly 10 minutes later. A 30-minute sample may also be collected.
The laboratory measures ACTH in these samples, and the veterinarian compares the post-TRH concentrations with appropriate seasonal reference intervals. A greater-than-expected rise supports a PPID diagnosis. [6]
Table 3. Example seasonal reference ranges for ACTH after TRH stimulation [6]
The following 2023 Equine Endocrinology Group values apply to the Immulite 2000xpi analyzer. From July through December, the test is most useful for identifying horses unlikely to have PPID because false-positive results are common.
| Sampling time | Time of year | PPID unlikely | Interpretive zone | PPID likely |
|---|---|---|---|---|
| 10 minutes after TRH | January to June | < 100 pg/mL | 100 to 200 pg/mL | > 200 pg/mL |
| 10 minutes after TRH | July to December | < 100 pg/mL | Highly variable; no reference interval established | |
| 30 minutes after TRH | January to June | < 40 pg/mL | 40 to 90 pg/mL | > 90 pg/mL |
| 30 minutes after TRH | July to December | < 40 pg/mL | Highly variable; no reference interval established | |
Treatment & Management
PPID is a condition that can be managed but not cured. The primary medication is pergolide, a dopamine agonist that activates dopamine receptors and helps restore inhibition of hormone production in the pars intermedia. Most treated horses show improvement in one or more PPID-associated clinical signs. [1]
Horses receiving pergolide need ongoing monitoring to assess their clinical response and determine whether the dose remains appropriate.
Current guidance recommends reassessing clinical signs, with endocrine testing when indicated, one to three months after treatment begins and then every six to 12 months. Testing in the same season each year makes ACTH trends easier to interpret. [6]
Extended-release cabergoline is another dopamine agonist that may be considered under veterinary direction where it is available. This intramuscular formulation has been used as an alternative when daily oral pergolide is not practical. [7]
Dietary Management
Dietary management depends on the horse’s body condition, insulin status, dental health, and ability to maintain muscle. Veterinarians often test horses with PPID for insulin dysregulation because concurrent hyperinsulinemia increases laminitis risk.
For horses with insulin dysregulation, a low-sugar, low-starch feeding program may include the following measures: [6]
- Follow a nutritionist-guided weight loss plan if the horse is overweight
- Limit grain-based concentrates, particularly those high in starch
- Select forage with low sugar (ESC) and starch content
- Restrict pasture access or use a properly fitted grazing muzzle
- Ensure the diet provides balanced vitamins and minerals without excess sugar or starch
These horses benefit from an individualized plan based on forage analysis, current weight, and metabolic status. The goal is to reduce excessive insulin responses while maintaining adequate forage intake and supplying essential nutrients.
For all horses with PPID, the diet should also address muscle loss, weight changes, and other clinical signs.
Management may include the following: [6][8]
- Provide adequate high-quality protein and essential amino acids to support muscle maintenance
- Add fat or other calorie sources when the horse needs to gain or maintain weight
- Adjust energy intake when the horse needs to lose weight
- Ensure unrestricted access to fresh water, particularly for horses that drink and urinate excessively
- Clip a long hair coat when needed to keep the horse comfortable in warm weather

Routine Health Care
Many horses with PPID are seniors and require consistent preventive care alongside medication and dietary management.
Their care program may include the following: [8]
- Provide suitable shelter during hot, cold, or inclement weather
- Schedule regular dental examinations and adapt the diet if chewing ability declines
- Use fecal testing and a veterinarian-guided deworming program
- Maintain regular hoof care and watch closely for early signs of laminitis
- Monitor and manage arthritis with veterinary guidance
- Arrange periodic veterinary examinations and bloodwork to monitor PPID and other age-related conditions
Tracking coat changes, appetite, water intake, body weight, muscle condition, soundness, and energy level can help owners and veterinarians evaluate how well the management plan is working.
Frequently Asked Questions
Here are some frequently asked questions about PPID in horses:
Equine Cushing's disease is the historical name for pituitary pars intermedia dysfunction (PPID), a common endocrine disorder in older horses. The condition affects the pituitary gland and causes abnormal production of several hormones.
Early signs can include delayed or incomplete shedding, subtle loss of topline muscle, lethargy, abnormal sweating, increased drinking and urination, or recurrent infections. These changes can have other causes, so veterinary assessment and diagnostic testing are important.
No. A long or abnormally retained coat is the most characteristic sign of PPID, but it does not occur in every affected horse. Horses with early PPID may have subtler signs, such as delayed shedding, muscle loss, altered fat distribution, or reduced energy.
PPID primarily affects older horses and is most often diagnosed after 15 years of age. Younger horses can occasionally develop the condition, so age alone does not exclude PPID.
Veterinarians diagnose PPID by considering the horse's age, history, clinical signs, and endocrine test results. Testing commonly includes a baseline ACTH measurement or a TRH stimulation test interpreted using season- and assay-specific reference intervals.
Yes. A horse in the early stages of PPID may have a baseline ACTH concentration within the reference range. If clinical suspicion remains high, the veterinarian may recommend repeat testing or a TRH stimulation test.
Yes. ACTH concentrations vary seasonally, so results must be interpreted using reference intervals appropriate for the time of year and laboratory assay. Testing during the same season each year can also make long-term ACTH trends easier to compare.
No. PPID and insulin dysregulation are separate endocrine conditions, although they can occur together. Horses with both conditions have a greater risk of laminitis, so veterinarians commonly assess insulin status when developing a PPID management plan.
There is no cure for PPID, but medication, nutrition, and preventive health care can help manage the condition and reduce the impact of its clinical signs.
The primary medication for PPID is pergolide, which helps restore dopaminergic control of the pars intermedia. Treated horses require ongoing monitoring, and the veterinarian may adjust the dose according to clinical response and endocrine test results.
Current guidance recommends reassessing clinical signs, with endocrine testing when indicated, one to three months after treatment begins and then every six to 12 months. Monitoring needs may vary based on the horse's response, test results, and other health concerns.
Horses with PPID and concurrent insulin dysregulation have an increased risk of laminitis. Assessing insulin status and managing hyperinsulinemia are therefore important parts of PPID care.
The diet should be tailored to the horse's insulin status, body condition, dental health, and ability to maintain muscle. Horses with insulin dysregulation generally need forage and feed that are appropriately low in sugar and starch while still providing adequate fiber, protein, vitamins, and minerals.
Diet is an important part of PPID management, especially when a horse also has insulin dysregulation, abnormal body condition, or difficulty maintaining muscle. However, dietary management does not replace veterinary diagnosis, prescribed medication, or ongoing monitoring.
Many horses with PPID maintain a good quality of life for years with appropriate medication, nutrition, dental and hoof care, parasite control, and veterinary monitoring.
Summary
Pituitary pars intermedia dysfunction is a common, progressive endocrine disorder in older horses that can often be managed successfully.
- PPID develops when degeneration of dopamine-producing neurons allows the pars intermedia to overproduce several hormones
- Delayed shedding, hypertrichosis, muscle loss, increased thirst and urination, and lethargy are common signs
- Concurrent insulin dysregulation substantially increases the risk of laminitis
- Diagnosis combines clinical findings with baseline ACTH or TRH stimulation testing interpreted against appropriate seasonal reference intervals
- Pergolide, individualized nutrition, and consistent preventive care support long-term management and quality of life
References
- Menzies-Gow. N. Equine Pituitary Pars Intermedia Dysfunction. Veterinary Sciences. 2025.
- McGowan. T.W. et al. Prevalence, risk factors and clinical signs predictive for equine pituitary pars intermedia dysfunction in aged horses. Equine Vet. J. 2013.
- Welsh. C.E. et al. Prevalence, survival analysis and multimorbidity of chronic diseases in the general veterinarian-attended horse population of the UK. Prev Vet Med. 2016.
- McGowan. C. Endocrinopathic Laminitis. Veterinary Clinics of North America: Equine Practice. 2010.
- Treiber. K.H. et al. Insulin Resistance in Equids: Possible Role in Laminitis. J Nutr. 2006.
- Hart. K. et al. Recommendations for the Diagnosis and Management of Pituitary Pars Intermedia Dysfunction (PPID). Equine Endocrinology Group. 2023.
- Sundra. T. et al. Retrospective Assessment of the Use of Extended-Release Cabergoline in the Management of Equine Pituitary Pars Intermedia Dysfunction. Frontiers in Veterinary Science. 2024.
- Geor. R. et al. Ed. Equine Applied and Clinical Nutrition: Health, Welfare and Performance. 1st ed. Saunders. 2013.




























